DISCLIFT for Disc Bulge
DISCLIFT is designed to manage spinal loading through controlled decompression. In appropriately selected individuals, this approach may assist with symptom tolerance and functional movement as part of a broader care plan.
Clinical suitability depends on:
- Location and size of the disc bulge
- Symptom behaviour and aggravating factors
- Neurological findings
- Overall spinal health and stability
DISCLIFT does not reverse disc bulges and does not guarantee symptom resolution.





Symptoms of a Disc Bulge
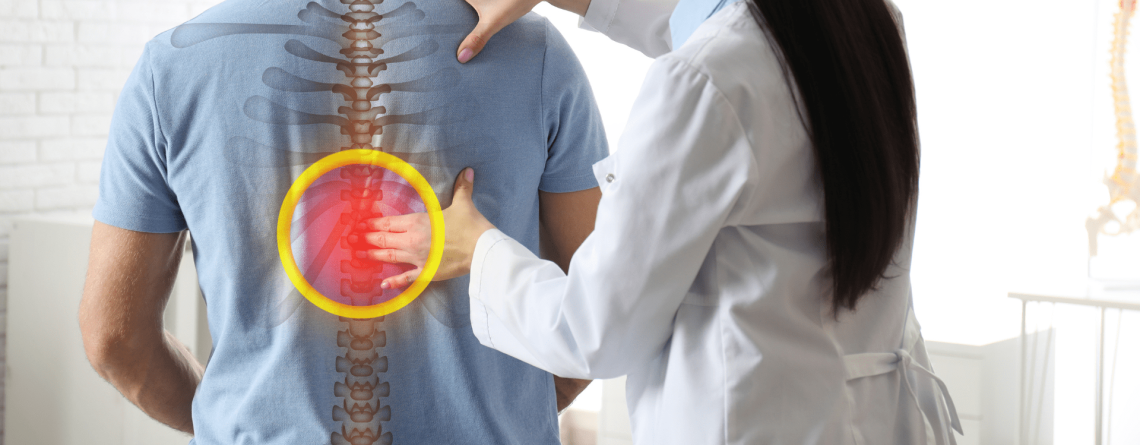
A disc bulge does not always cause symptoms. Many disc changes appear on imaging without creating pain or loss of function. Symptoms are more relevant when the disc change affects nearby spinal structures or appears consistent with the person’s clinical presentation. Possible symptoms include:- Localised neck or back discomfort
- Pain extending into an arm or leg
- Tingling or altered sensation
- Numbness
- Reduced tolerance for sitting, bending, lifting, or prolonged positions
- Weakness where nerve function is affected
What Causes a Disc Bulge?
Disc bulges commonly occur alongside normal age-related changes in spinal discs. Over time, discs may lose hydration and flexibility, which changes how they respond to repeated loading. Physical work, repeated bending or lifting, previous spinal strain, smoking, and individual spinal health may also contribute. A disc bulge does not always result from one specific event.Disc Bulge vs Disc Herniation
A disc bulge generally involves a broader extension of disc tissue beyond the usual disc boundary. A disc herniation refers to a more localised displacement of disc material. Both findings range in severity and may appear with or without symptoms. A scan alone does not establish whether either finding is responsible for pain. Assessment needs to consider symptom behaviour, neurological findings, function, and other possible causes.How Is a Disc Bulge Diagnosed?
Assessment usually starts with your symptoms and medical history. A clinician will ask where you feel discomfort, whether symptoms travel into an arm or leg, which movements aggravate the problem, and whether numbness or weakness is present. Physical examination may include spinal movement, strength, sensation, reflexes, and functional tasks. MRI or other imaging may be requested when the findings support further investigation. Imaging is not required for every episode of neck or back pain. Existing scans also need to be interpreted alongside the clinical examination because disc bulges are sometimes present in people without symptoms.Treatment Options for a Disc Bulge
Management depends on the symptoms rather than the imaging label alone. Options may include:- Remaining active within tolerable limits
- Exercise and rehabilitation
- Physiotherapy or other clinically appropriate movement-based care
- Activity or workload modification
- Medicines discussed with a GP or pharmacist
- Medical review where symptoms persist or neurological changes are present
- Specialist assessment where symptoms are severe, progressive, or fail to respond to conservative care
When Should You Seek Medical Attention?
Arrange medical assessment when back or neck symptoms continue to worsen, interfere with normal activities, or occur with persistent numbness, tingling, or weakness. Urgent medical assessment is required for symptoms such as loss of bladder or bowel control, difficulty passing urine, numbness around the genital or anal region, rapidly increasing weakness, significant loss of movement, fever with spinal pain, or symptoms following serious trauma. People with these findings should receive medical review before considering routine decompression treatment.FAQs
Is a disc bulge the same as a herniation?
No. A disc bulge involves outward extension of the disc without rupture, while a herniation involves displacement of disc material. Suitability for decompression varies between individuals.
Can decompression fix a disc bulge ?
Spinal decompression may help reduce discomfort associated with a disc bulge and support better spinal movement.
It doesn’t necessarily “fix” or reverse the disc bulge itself, and results vary from person to person.
A proper assessment can help determine whether decompression is suitable for your symptoms.
Does every disc bulge require treatment?
No. Disc bulges frequently appear without symptoms. Treatment depends on the clinical presentation rather than the imaging finding alone.
Does a disc bulge always become a herniation?
No. A disc bulge does not automatically progress to a herniation. Disc findings and symptoms vary between individuals over time.
Can I exercise with a disc bulge?
Movement and exercise often form part of conservative management, although the type and intensity should suit your symptoms and physical capacity.
Do I need a scan for a disc bulge?
Not in every case. A clinician may recommend imaging where symptoms, neurological findings, trauma, or other clinical factors support further investigation.
Can DISCLIFT reverse a disc bulge?
No. DISCLIFT does not reverse or repair disc tissue. Controlled decompression may be considered as one component of a broader management plan for selected individuals.
How is progress reviewed during treatment?
Progress is assessed through changes in symptoms, movement tolerance, function, neurological findings where relevant, and response to the management plan. Treatment is adjusted according to those findings.
Evidence, Safety and Responsibility
Research into spinal decompression therapy continues to evolve.
Some studies suggest potential benefits for carefully selected individuals, while others highlight variability in outcomes and emphasise the importance of screening, controlled delivery, and realistic expectations
Health policy reviews consistently note that spinal decompression therapy should not be positioned as a cure or universal solution.
DISCLIFT is offered as an evidence-informed option within a structured clinical framework. It does not replace medical or surgical care.